
Patients with cholangiocarcinoma face
a poor prognosis1
What is cholangiocarcinoma?
CCA is a highly aggressive, rapidly progressing and heterogeneous malignancy arising from the epithelial cells of the biliary tree.1,2 Mortality closely mirrors incidence, making it one of the most lethal malignancies and an increasingly important health concern.2 Although still rare, its global incidence continues to rise, driven by increasing risk factors and advances in detection.2,3
Clinical presentation
CCA is often asymptomatic in its early stages.1 When symptoms do occur, they are typically non-specific (including asthenia, abdominal pain, malaise, nausea, anorexia and weight loss), which frequently delays diagnosis.1 As a result, most patients present with advanced disease and are ineligible for potentially curative surgery.1 Consequently, the median overall survival for patients with unresectable disease remains under one year.3
Understand the key signs and symptoms of CCA – download Spotting the Red Flags today
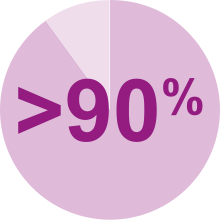
of patients with advanced CCA are not expected to
live beyond 5 years4

Although rare, the incidence of CCA, including
intrahepatic cholangiocarcinoma, is steadily increasing
worldwide1
Patients with cholangiocarcinoma face a number of treatment challenges1,5,6
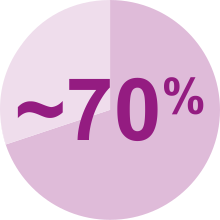
of patients with CCA are diagnosed
at an advanced stage, limiting
treatment options1

of patients with intrahepatic CCA
who undergo surgery experience
disease recurrence within 24
months5

Patients with CCA experience a
rapid decline in health-related quality
of life due to both disease- and
treatment-related symptoms6
Anatomical classification
CCA is classified according to its anatomical origin.2
- Intrahepatic CCA (iCCA) arises in the bile ducts within the liver2
- Extrahepatic CCA (eCCA) arises in the bile ducts outside the liver:2
- Perihilar CCA (pCCA) develops at the junction of the left and right hepatic ducts
- Distal CCA (dCCA) occurs in the common bile duct beyond the hepatic duct confluence

These anatomical subtypes differ not only in location and clinical presentation, but also in their underlying molecular characteristics.2
Molecular alterations by subtype
CCA is genetically heterogeneous, with distinct molecular alteration patterns across its anatomical subtypes.2
Understanding these differences is increasingly important for assessing prognosis and therapeutic decision-making.2
IDH1/2
KRAS
TP53
FGFR2
BRAF
ERBB2/3
Adapted from Banales JM, et al. 2026.2
Clinical relevance
iCCA more commonly harbours targetable alterations such as IDH1/2 mutations and FGFR2 fusions, compared with the other subtypes.2
IDH1/2
KRAS
TP53
FGFR2
BRAF
ERBB2/3
Adapted from Banales JM, et al. 2026.2
Clinical relevance
Molecular features of pCCA overlap with distal CCA, with fewer targetable kinase fusions compared with iCCA.2
IDH1/2
KRAS
TP53
FGFR2
BRAF
ERBB2/3
Adapted from Banales JM, et al. 2026.2
Clinical relevance
dCCA is characterised predominantly by established oncogenic drivers such as KRAS and TP53.2
Learn more about CCA symptoms, risks and treatment options – download CCA at a Glance now
CCA, cholangiocarcinoma; dCCA, distal cholangiocarcinoma; eCCA, extrahepatic cholangiocarcinoma; FGFR, fibroblast growth factor receptor; iCCA, intrahepatic cholangiocarcinoma; IDH, isocitrate dehydrogenase; pCCA, perihilar cholangiocarcinoma.
References: 1. Banales JM, et al. Nat Rev Gastroenterol Hepatol. 2020;17(9):557–588; 2. Banales JM, et al. Nat Rev Gastroenterol Hepatol. 2026;23(1):65–96; 3. Izquierdo-Sanchez L, et al. J Hepatol. 2022;76(5):1109–1121; 4. Goyal L, et al. Cancer Treat Rev. 2021;95:102170; 5. Choi WJ, et al. Ann Surg Oncol. 2022;29:4337–4353; 6. Hunter LA, Soares HP. Cancers (Basel). 2021;13(20):5074.